High blood pressure often travels with metabolic disease. Here is the treatment plan first, followed by the measurements and evidence behind it.
On this page
The Protocol
Start here. Use home readings and your clinical history to guide these actions. The evidence and details follow under The Reasoning.
- Start a well-formulated low-carbohydrate eating plan. Cut sugary drinks and refined starches; build meals around adequate protein, non-starchy vegetables and minimally processed foods. If you have excess weight, pursue sustained weight loss. Why this comes early
Observed systolic change: About 10 mm Hg lower after four months in one low-carbohydrate trial of adults with hypertension, excess weight and prediabetes or type 2 diabetes; weight loss averages about 1 mm Hg per kilogram lost. These effects overlap. Low-carbohydrate trial · Weight-loss evidence
- Consider intermittent fasting or a consistent eating window. Add it when appropriate for you. Fasting details
Observed systolic change: About 2 mm Hg lower than unrestricted eating across one pooled analysis of time-restricted-eating trials in adults without diabetes. The additional effect alongside low-carb care is not established. Trial analysis
- Move regularly. Work toward 90–150 minutes a week of aerobic activity, with resistance training as appropriate. Build up progressively. Exercise details
Observed systolic change: About 4–8 mm Hg lower with structured aerobic exercise in adults with hypertension. Exercise evidence
- Protect sleep and check for sleep apnea. If you snore, wake gasping, feel sleepy during the day, or your blood pressure is hard to control, ask about evaluation. Sleep-study options
Observed systolic change: A sleep study diagnoses apnea; it does not lower pressure by itself. Among people with resistant hypertension and confirmed apnea, CPAP lowered 24-hour systolic pressure by about 5 mm Hg across trials. CPAP trial analysis
- Increase potassium and magnesium; address other pressure drivers. Eat more potassium-rich low-carbohydrate foods, including avocado, leafy greens and fish. Add magnesium glycinate as the magnesium supplement in this plan. Reduce heavy alcohol use; stop tobacco and nicotine. Nutrition and electrolyte details
Observed systolic change: Increased potassium intake: about 5–6 mm Hg lower in hypertensive trial groups; magnesium supplementation: about 2–3 mm Hg lower across studied forms; substantially reducing very heavy alcohol intake: about 5.5 mm Hg lower. Potassium trials · Magnesium trials · Alcohol trials
- Measure, review medication and track the response. Use a validated upper-arm cuff and record repeated home readings before and during changes. Medication may still be needed; use your log to see how pressure responds. How to measure · Medication decisions
Observed systolic change: Measuring and reviewing do not directly lower pressure. When indicated, one standard-dose blood-pressure medicine lowered systolic pressure by about 9 mm Hg versus placebo on average across trials; individual responses vary. Medication trial analysis
These estimates come from different populations and timeframes. Benefits can overlap and should not be added into a promised total.
The Reasoning
High blood pressure often causes no obvious symptoms, but over time it can damage blood vessels and increase the risk of heart attack, stroke, heart failure, kidney disease and cognitive decline. That is why measuring it accurately—and treating the whole person rather than reacting to one isolated reading—matters.
Blood pressure is influenced by genetics, age, kidney function, medications, sleep, stress, body composition, physical activity, dietary patterns, kidney and electrolyte balance, alcohol intake and metabolic health. Insulin resistance can be part of this picture, but it is not the only cause of hypertension.
The encouraging part is that blood pressure is modifiable. Lifestyle treatment can make a meaningful difference, and medication can reduce risk when lifestyle changes are not enough or a person’s overall cardiovascular risk is high. These approaches work together rather than competing with each other.
Measure accurately
How to measure blood pressure at home
Home readings can help confirm hypertension, identify white-coat or masked hypertension and show whether treatment is working. The American Heart Association recommends a validated automatic upper-arm cuff rather than a wrist, finger or unvalidated cuffless device.[2]
For a useful home reading:
- Avoid caffeine, smoking and exercise for at least 30 minutes beforehand.
- Empty your bladder and sit quietly for five minutes.
- Sit with your back supported and feet flat on the floor.
- Place the cuff on bare skin and support the arm at heart level.
- Do not talk, text or move during the measurement.
- Take two readings one minute apart and record both.
- Measure at consistent times according to the plan you made with your clinician.
Correct cuff size matters. A cuff that is too small or too large can give a misleading result. Bring your monitor to a clinical visit so the team can confirm its fit and accuracy.[2]
Understand the readings
What the two blood-pressure numbers mean
A blood-pressure reading contains two numbers, measured in millimeters of mercury (mm Hg):
- Systolic pressure is the top number. It reflects the pressure in the arteries when the heart contracts.
- Diastolic pressure is the bottom number. It reflects the pressure while the heart relaxes between beats.
For example, a reading of 120/80 mm Hg means a systolic pressure of 120 and a diastolic pressure of 80.
The 2025 American Heart Association and American College of Cardiology guideline classifies blood pressure in adults as follows:[1]
| Category | Systolic | Diastolic |
|---|---|---|
| Normal | Less than 120 | and less than 80 |
| Elevated | 120–129 | and less than 80 |
| Stage 1 hypertension | 130–139 | or 80–89 |
| Stage 2 hypertension | 140 or higher | or 90 or higher |
A diagnosis should generally be based on properly obtained readings from more than one occasion, often supported by home or ambulatory monitoring. One elevated measurement does not tell the entire story.
Why blood pressure and metabolic health matter
Why high blood pressure matters
As blood pressure rises, cardiovascular risk generally rises with it. The amount of risk depends on more than the blood-pressure number alone. Age, smoking, diabetes, kidney disease, cholesterol and lipoprotein levels, existing cardiovascular disease, family history and other factors all affect the likely benefit of treatment.
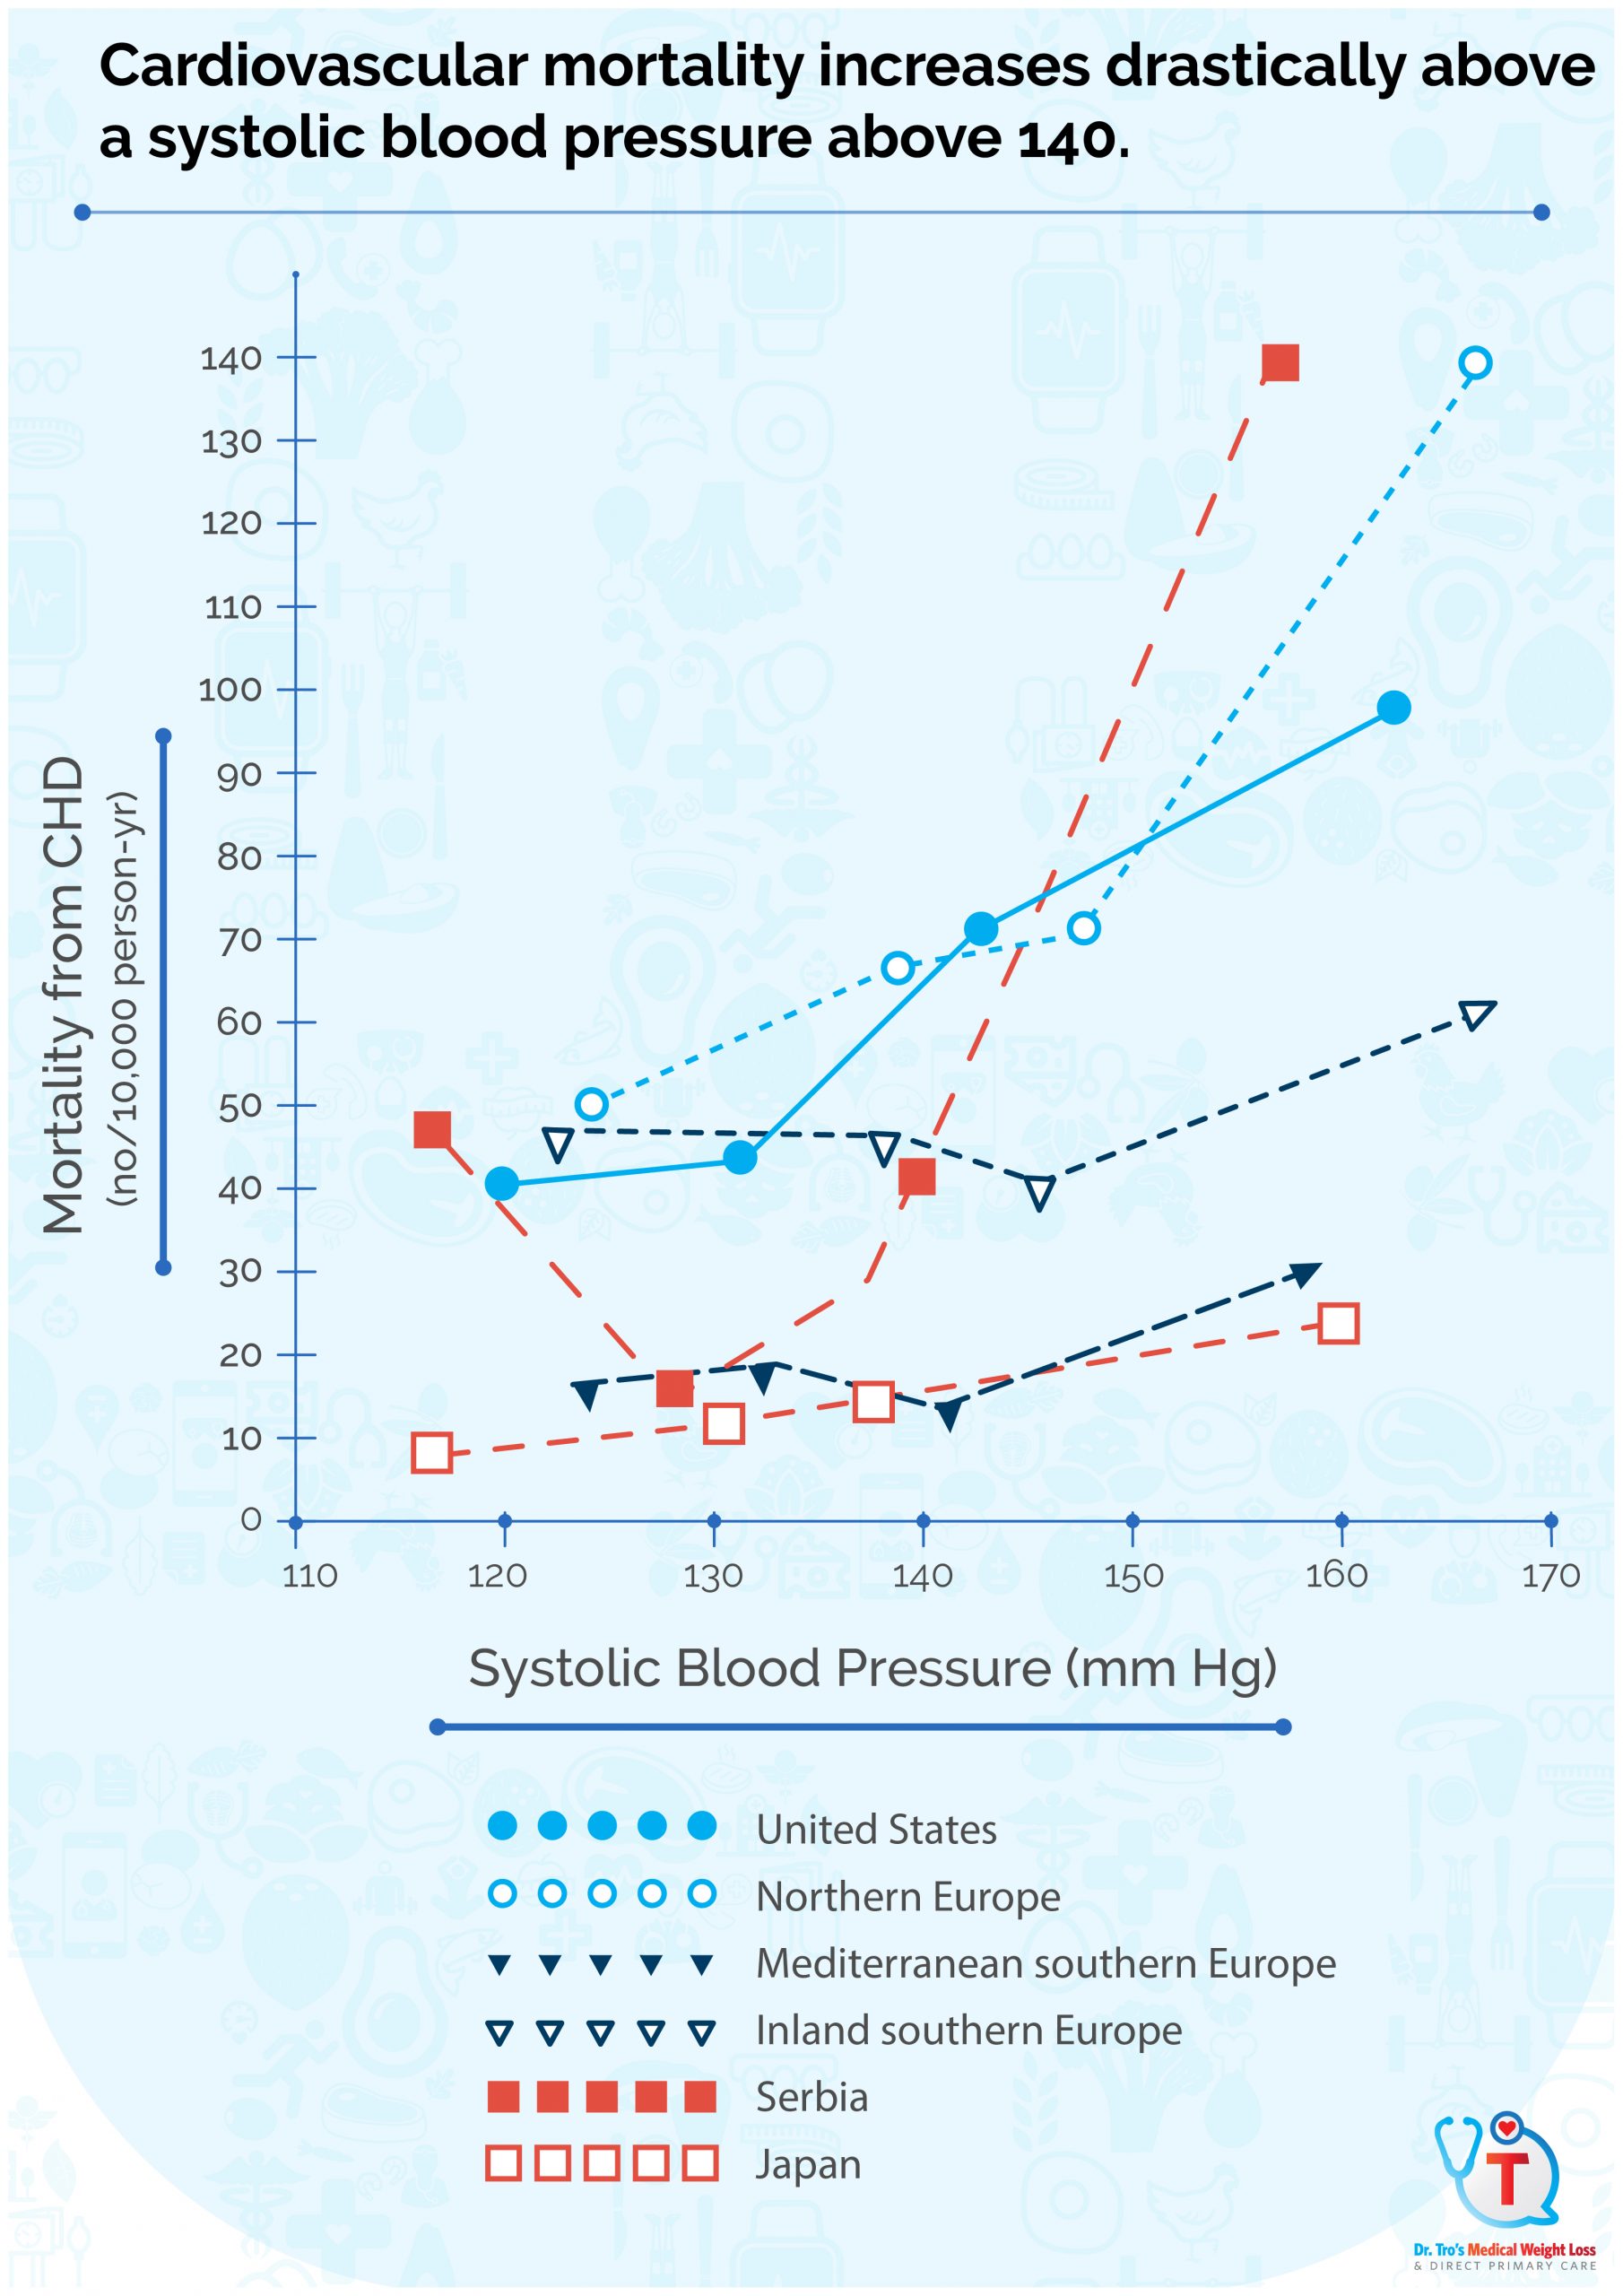
The 2025 guideline identifies a treatment goal below 130/80 mm Hg for most adults, while emphasizing individualized decisions for people who are pregnant, frail, living in an institution or facing a limited life expectancy.[1]
Medication is recommended alongside lifestyle treatment for adults with average blood pressure of 140/90 mm Hg or higher. It is also recommended at lower levels for selected people with cardiovascular disease, previous stroke, diabetes, chronic kidney disease or sufficiently elevated predicted cardiovascular risk. For lower-risk adults with stage 1 hypertension, clinicians may begin with lifestyle treatment and reassess after three to six months.[1]
The connection between hypertension and metabolic health
Hypertension commonly travels with abdominal adiposity, elevated glucose, high triglycerides, fatty liver and other features of insulin resistance. Several biological pathways may contribute, including increased sympathetic nervous-system activity, altered kidney handling of fluid and electrolytes, vascular dysfunction and hormonal signaling.
This relationship does not mean that every case of hypertension is caused by insulin resistance. Kidney disease, sleep apnea, thyroid or adrenal disorders, medications, alcohol, genetics and other conditions may contribute. Very high, sudden, treatment-resistant or unusually early hypertension deserves a careful clinical evaluation.
What long-term studies show
In the 20-year CARDIA study of 3,413 young adults without hypertension at baseline, those in the highest fasting-insulin quartile had an 85% higher adjusted hazard of developing hypertension than those in the lowest quartile (hazard ratio 1.85).[10] In MESA, among 3,513 adults initially without hypertension, each doubling of fasting insulin was associated with a 15% higher adjusted rate of new hypertension over a median 4.7 years.[11] Fasting insulin is one marker of metabolic health; these prospective associations support looking beyond the blood-pressure reading.
Blood pressure also tracks with coronary artery calcium (CAC), which measures calcified plaque in the coronary arteries. In another CARDIA analysis, after 25 years a CAC score of 100 or more was present in 4.0% of people in the low, stable blood-pressure trajectory, 17.4% in the elevated, stable trajectory and 25.4% in the elevated, rising trajectory. The association remained after adjustment for factors including body mass index, diabetes, cholesterol and smoking.[12] This does not show that lowering blood pressure reverses an existing CAC score.
Companion video
How Blood Pressure Relates to Insulin Resistance
Why low-carb eating and fasting come early
Early starts: When high blood pressure occurs with insulin resistance, prediabetes, type 2 diabetes or excess weight, a sustainable, well-formulated low-carbohydrate eating pattern is a recommended early option. Intermittent fasting or a consistent time-restricted eating window can be another early step when appropriate. Track home blood pressure as you start. See the metabolic and CAC data, low-carb evidence and fasting guidance below.
Address insulin resistance and excess weight when present
Losing excess body weight often lowers blood pressure. For some people with insulin resistance, prediabetes or type 2 diabetes, a well-formulated low-carbohydrate approach can improve weight, glucose regulation and blood pressure.
In a randomized trial of adults with hypertension plus prediabetes or type 2 diabetes, a very-low-carbohydrate intervention produced a larger average reduction in systolic blood pressure, weight and A1c than the comparison diet over four months.[8] This does not prove that one diet is best for everyone. It does show that therapeutic carbohydrate reduction can be a reasonable evidence-based option when it fits the patient’s needs and can be followed safely.
An earlier observational study from a UK primary-care practice also reported sustained improvements in blood pressure, weight and lipid measures among insulin-resistant patients using a carbohydrate-restricted diet.[4] Because that study was observational, it cannot separate the diet’s effect from weight loss, medication changes, clinical support or other factors.
A smaller randomized study in women with obesity examined vascular function during low-carbohydrate weight loss and found that the observed changes were not dependent on prescribing an additional calorie restriction.[7] This informs the vascular discussion but does not establish that carbohydrate restriction alone will control hypertension.
Use fasting carefully
Time-restricted eating or intermittent fasting may help some people improve weight and metabolic health. A randomized trial in stage 1 hypertension found that adding time-restricted eating to the comparison dietary program improved outcomes.[9] Fasting is an option rather than a requirement.
Blood-pressure results from Toward Health care
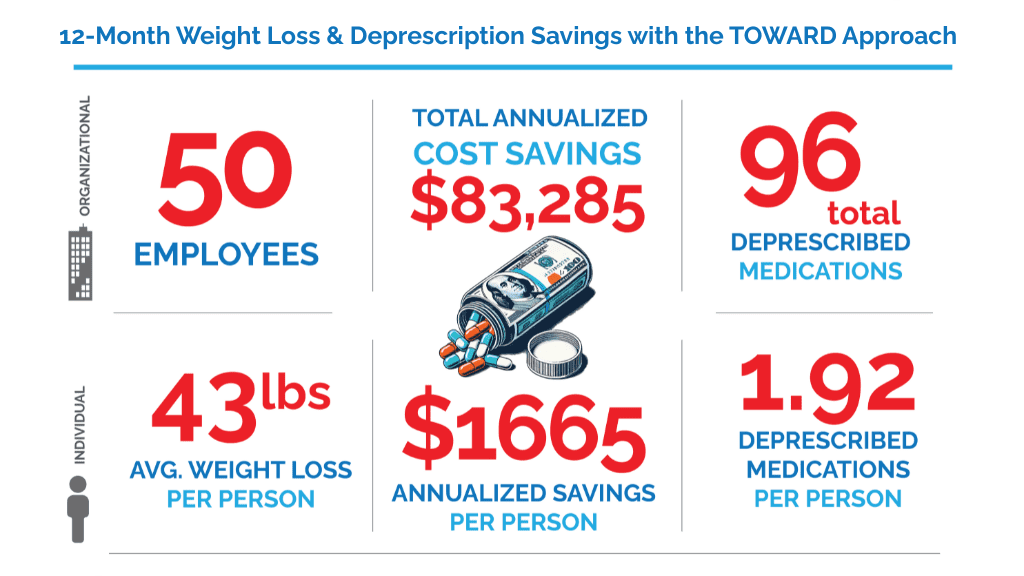
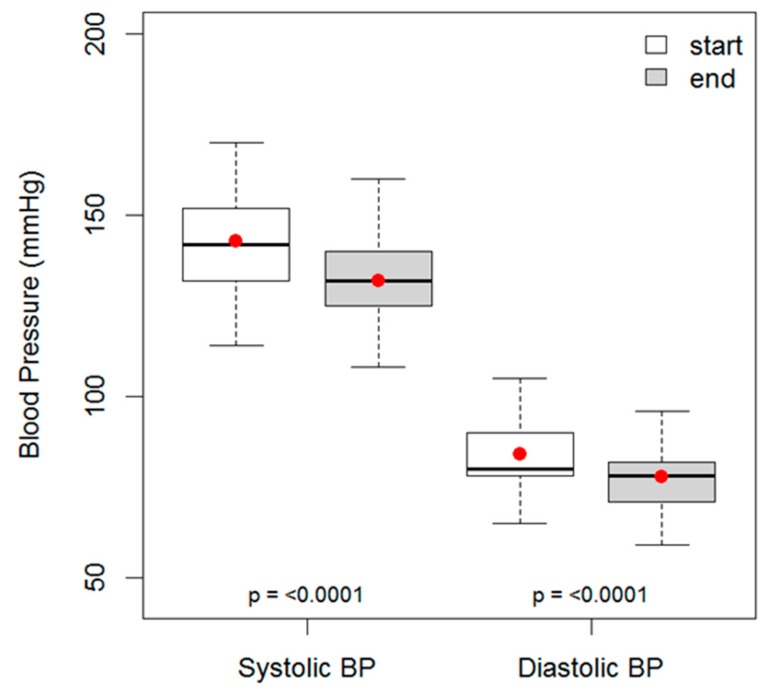
In a published six-month Toward Health pilot, mean systolic pressure among 10 employees receiving carbohydrate-restricted metabolic care fell from 141 to 124 mm Hg, a 17 mm Hg decrease. The median fell from 140 to 121 mm Hg.
Toward Health’s summary of its newer one-year, 120-adult study reports a 10.7 mm Hg reduction in systolic pressure; 90 participants had paired data for the primary cardiovascular-risk analysis. The peer-reviewed study reports estimated risk, not a count of heart attacks. These blood-pressure changes were observed during comprehensive care with nutrition, clinical support and monitoring; they are not separate expected reductions for each action above.
Evidence behind the treatment steps
Lifestyle strategies that can lower blood pressure
How much can each step lower systolic pressure?
Studies and the 2025 AHA/ACC guideline report these changes in systolic blood pressure:
- Lose excess weight: In a meta-analysis of 25 randomized trials, systolic pressure fell an average of 1.05 mm Hg per kilogram (2.2 lb) of weight lost.[14]
- Cut sugary drinks: In a prospective analysis of 810 adults, one fewer 12-ounce sugar-sweetened beverage per day was associated with 1.8 mm Hg lower systolic pressure over 18 months.[15]
- Do regular cardio: The guideline reports an average 4–8 mm Hg reduction with 90–150 minutes a week of structured aerobic exercise for adults with hypertension.[1]
- Use HIIT when suitable: In a randomized trial of 88 adults with hypertension, supervised high-intensity intervals lowered 24-hour systolic pressure by 12 mm Hg from baseline after 12 weeks, compared with 4.5 mm Hg for moderate continuous exercise.[16]
Improve the overall dietary pattern
Start with a sustainable, well-formulated low-carbohydrate pattern built around minimally processed foods, adequate protein, non-starchy vegetables and other nutrient-dense foods appropriate for the individual. Cutting sugary drinks and excess refined starch belongs early in this plan. Increase potassium-rich foods and use magnesium glycinate as the magnesium supplement in this plan. Limiting alcohol can also help.[1]
Increase potassium-rich foods such as avocado, leafy greens and fish. Magnesium glycinate is the recommended magnesium supplement for this protocol; check the elemental magnesium amount on the label. Higher potassium intake lowered systolic pressure by about 5–6 mm Hg in hypertensive trial groups, while magnesium supplements across studied forms lowered it by about 2–3 mm Hg. Potassium trials · Magnesium trials
Move regularly
Aerobic activity, resistance training and reducing prolonged sedentary time can lower blood pressure and improve insulin sensitivity. The best program is one a person can perform consistently, building up over time.
In a 12-week randomized trial of adults with resistant hypertension, three supervised 40-minute moderate-intensity aerobic sessions each week lowered 24-hour systolic blood pressure by 7.1 mm Hg more than usual care.[13] This small trial illustrates a possible benefit; it does not predict the response for every person.
Protect sleep and address sleep apnea
Insufficient sleep and untreated obstructive sleep apnea can make hypertension harder to control. Loud snoring, witnessed pauses in breathing, morning headaches, persistent daytime sleepiness or blood pressure that remains hard to control should prompt a conversation with a clinician. Toward Health offers an at-home sleep study when a clinician determines that home testing is appropriate; some people need a different evaluation. The Sleep Protocol covers sleep routines in more detail.
Reduce alcohol and stop smoking
Reducing or eliminating alcohol can improve blood pressure. Smoking does not always produce sustained hypertension on a routine office measurement, but it acutely raises blood pressure and greatly increases cardiovascular risk. Avoiding tobacco and nicotine remains essential.
Medication remains an important tool
Lifestyle treatment should be offered to everyone with elevated blood pressure, but it does not eliminate the need for medication when risk remains high or blood pressure stays above target.
The SPRINT trial found that intensive systolic blood-pressure treatment reduced cardiovascular events and mortality in selected adults at elevated cardiovascular risk without diabetes or prior stroke.[5, 6] Intensive treatment also produced more adverse events of certain types, which is one reason targets and medication plans should be individualized.
The right regimen depends on the person’s blood-pressure pattern, kidney function, other medical conditions, pregnancy status, medication tolerance and overall cardiovascular risk. Many people require more than one medication.
If lifestyle changes lead to substantial weight loss or metabolic improvement, medication needs may change. Closer monitoring can reveal the response.
Monitor and adjust
Keep recording home readings as your nutrition, activity, sleep or medication plan changes. Use the pattern, symptoms, medication effects, weight and metabolic changes to assess the response.
The practical takeaway
High blood pressure is both a cardiovascular issue and, for many people, part of a broader metabolic-health pattern. The most useful plan combines accurate measurement, assessment of overall risk, treatment of contributing conditions and sustainable lifestyle changes. Medication should be used when its expected benefits outweigh its risks, and it should be adjusted as health circumstances change.
The goal is not to chase one perfect reading. It is to reduce long-term risk safely and consistently.
For more background on blood-pressure numbers, home measurement and metabolic health, read High Blood Pressure and Metabolic Health: What the Numbers Mean and What Helps. This protocol puts the actions first; that article explains the findings in more detail.
References
Guidelines and patient resources
- Jones DW, Ferdinand KC, Taler SJ, et al. 2025 AHA/ACC/AANP/AAPA/ABC/ACCP/ACPM/AGS/AMA/ASPC/NMA/PCNA/SGIM Guideline for the Prevention, Detection, Evaluation, and Management of High Blood Pressure in Adults. Circulation. Published online August 14, 2025. doi: 10.1161/CIR.0000000000001356. Official guideline hub ↩1↩2↩3↩4↩5↩6
- American Heart Association. Home Blood Pressure Monitoring. Reviewed August 14, 2025. https://www.heart.org/en/health-topics/high-blood-pressure/understanding-blood-pressure-readings/monitoring-your-blood-pressure-at-home ↩1↩2↩3↩4
Source references
- Prospective Studies Collaboration. Age-specific relevance of usual blood pressure to vascular mortality: a meta-analysis of individual data for one million adults in 61 prospective studies. Lancet. 2002;360(9349):1903–1913. doi: 10.1016/S0140-6736(02)11911-8.
- Unwin DJ, Tobin SD, Murray SW, Delon C, Brady AJ. Substantial and Sustained Improvements in Blood Pressure, Weight and Lipid Profiles from a Carbohydrate Restricted Diet: An Observational Study of Insulin Resistant Patients in Primary Care. Int J Environ Res Public Health. 2019;16(15):2680. doi: 10.3390/ijerph16152680 ↩
- SPRINT Research Group, Wright JT Jr, Williamson JD, et al. A Randomized Trial of Intensive versus Standard Blood-Pressure Control. N Engl J Med. 2015;373:2103–2116. doi: 10.1056/NEJMoa1511939 ↩
- SPRINT Research Group, Lewis CE, Fine LJ, et al. Final Report of a Trial of Intensive versus Standard Blood-Pressure Control. N Engl J Med. 2021;384(20):1921–1930. doi: 10.1056/NEJMoa1901281 ↩
- Hwang CL, Ranieri C, Szczurek MR, et al. The Effect of Low-Carbohydrate Diet on Macrovascular and Microvascular Endothelial Function Is Not Affected by the Provision of Caloric Restriction in Women with Obesity: A Randomized Study. Nutrients. 2020;12(6):1649. doi: 10.3390/nu12061649 ↩
- Saslow LR, Jones LM, Sen A, et al. Comparing Very Low-Carbohydrate vs DASH Diets for Overweight or Obese Adults With Hypertension and Prediabetes or Type 2 Diabetes: A Randomized Trial. Ann Fam Med. 2023;21(3):256–263. doi: 10.1370/afm.2968 ↩
- Zhou X, Lin X, Yu J, et al. Effects of DASH diet with or without time-restricted eating in the management of stage 1 primary hypertension: a randomized controlled trial. PubMed record ↩
- Xun P, et al. Fasting Insulin Level Is Positively Associated With Incidence of Hypertension Among American Young Adults: A 20-year follow-up study. Diabetes Care. 2012;35(7):1532–1537. doi: 10.2337/dc11-2443 ↩
- Levin G, et al. Glucose, insulin, and incident hypertension in the Multi-Ethnic Study of Atherosclerosis. Am J Epidemiol. 2010;172(10):1144–1154. doi: 10.1093/aje/kwq266 ↩
- Allen NB, et al. Blood Pressure Trajectories in Early Adulthood and Subclinical Atherosclerosis in Middle Age. JAMA. 2014;311(5):490–497. doi: 10.1001/jama.2013.285122 ↩
- Lopes S, Mesquita-Bastos J, Garcia C, et al. Effect of Exercise Training on Ambulatory Blood Pressure Among Patients With Resistant Hypertension: A Randomized Clinical Trial. JAMA Cardiol. 2021;6(11):1317–1323. doi: 10.1001/jamacardio.2021.2735 ↩
- Neter JE, Stam BE, Kok FJ, Grobbee DE, Geleijnse JM. Influence of weight reduction on blood pressure: a meta-analysis of randomized controlled trials. Hypertension. 2003;42(5):878–884. doi: 10.1161/01.HYP.0000094221.86888.AE ↩
- Chen L, Caballero B, Mitchell DC, et al. Reducing consumption of sugar-sweetened beverages is associated with reduced blood pressure: a prospective study among United States adults. Circulation. 2010;121(22):2398–2406. doi: 10.1161/CIRCULATIONAHA.109.911164 ↩
- Molmen-Hansen HE, Stolen T, Tjonna AE, et al. Aerobic interval training reduces blood pressure and improves myocardial function in hypertensive patients. Eur J Prev Cardiol. 2012;19(2):151–160. doi: 10.1177/1741826711400512 ↩
Important: If an unexpected reading remains above 180/120 mm Hg after one minute, call 911 for chest pain, breathing trouble, weakness, speech or vision changes, or confusion.[2] Otherwise, contact a clinician promptly; do not take extra blood-pressure medicine without their direction.[1, 2] Discuss this plan, supplements, fasting, exercise and medication changes with your own doctor or clinical team. If you take insulin, sulfonylureas, diuretics or blood-pressure medicine, glucose or pressure may fall during diet change, fasting or weight loss, and doses may need adjustment. If you have kidney disease or take medicines that affect potassium, review a deliberate potassium increase with your clinician and ask about magnesium supplementation if kidney function is reduced. Do not change prescribed doses on your own. Reading this page does not establish a doctor-patient relationship with Toward Health.