Have you ever finished a large meal, felt full, and then found yourself searching for food again only a few hours later?
The leftover pizza suddenly looks better than it did when it was fresh. Dessert sounds appealing even though your stomach is not empty. You may interpret that urge as a lack of willpower, but eating behavior is shaped by more than conscious intention. One important signal is what your blood sugar does after a meal.
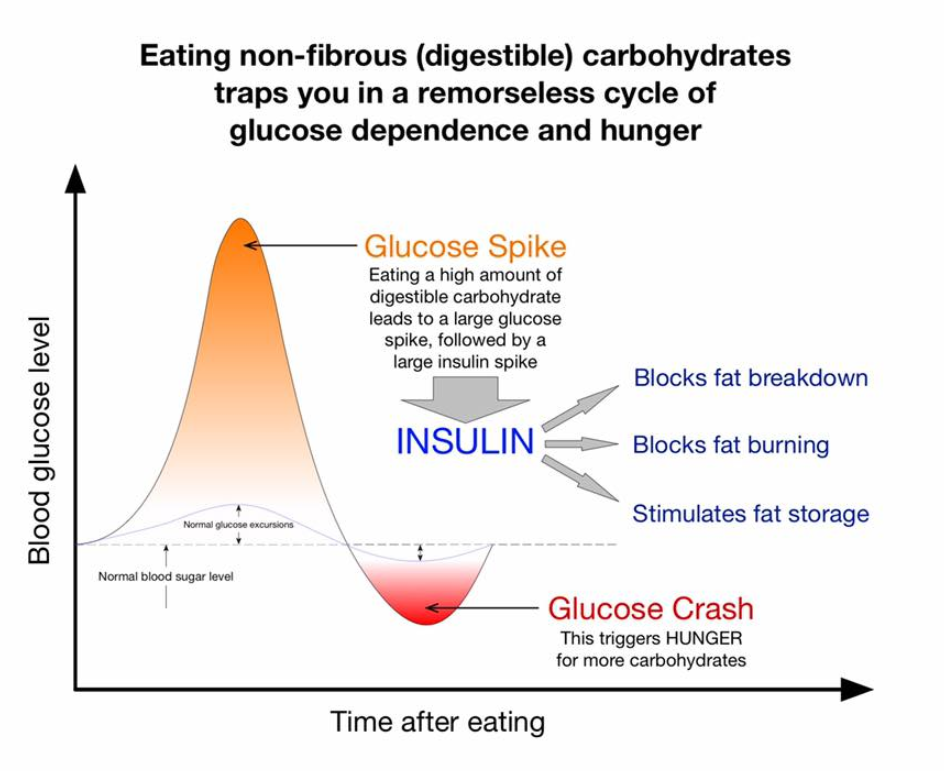
Some meals produce a rapid rise in glucose followed by a pronounced decline. That post-meal dip can increase hunger, make highly rewarding foods more appealing, shorten the time until the next meal, and increase how much a person eats later in the day.[1, 2, 3, 4, 5, 6, 7, 8]
This does not mean that every craving is caused by blood sugar. Stress, inadequate sleep, learned cues, food reward, emotions, social context, and food addiction can each create a desire to eat. But when glucose rises and falls sharply, biology can amplify those other pressures. Understanding that mechanism helps replace self-blame with a more useful question:
What happened before I became hungry again?
On this page
What glycemia and glycemic variability mean
Glycemia simply means the amount of glucose in the blood.
Glycemic variability describes how much glucose rises and falls over time. It can refer to changes within a day, differences between days, or longer-term variation in measures such as A1C. Those measurements are related, but they are not interchangeable.
For hunger, the most relevant pattern is often the movement after a meal. A meal that produces a high peak followed by a rapid fall can feel very different from one that produces a smaller, steadier response. The glucose level does not have to meet the medical definition of hypoglycemia for the direction and speed of change to matter to appetite.[5, 7, 8]
That is why two meals with similar calories can create very different experiences several hours later.
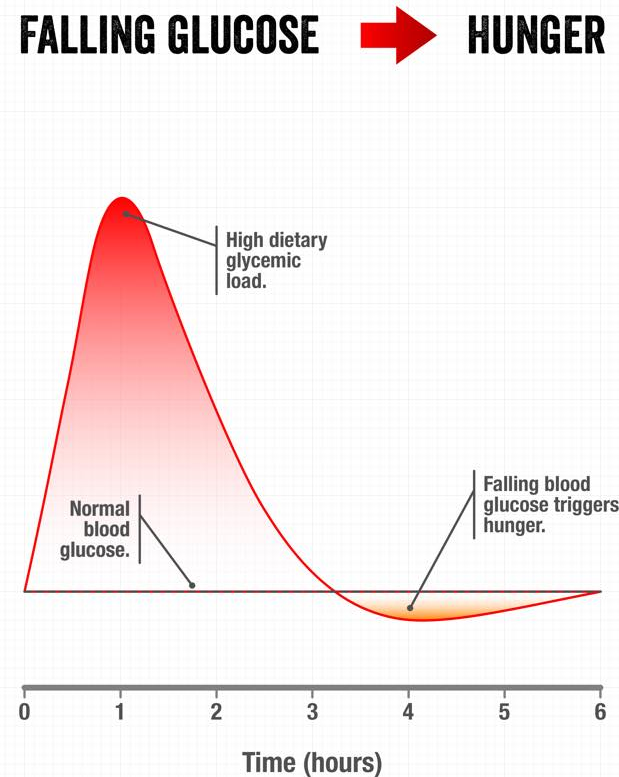
The connection between falling glucose and eating is not new
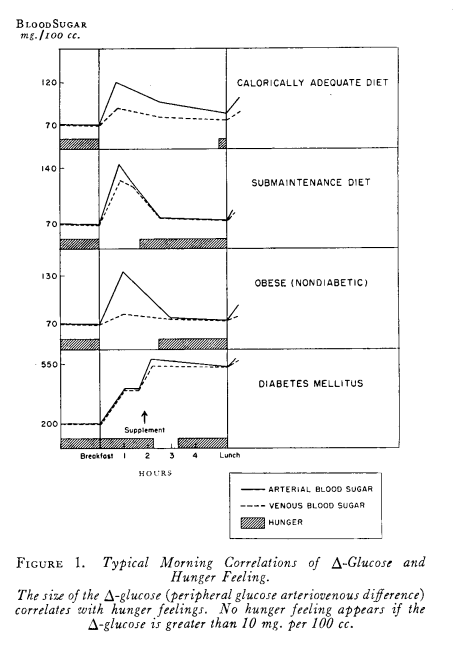
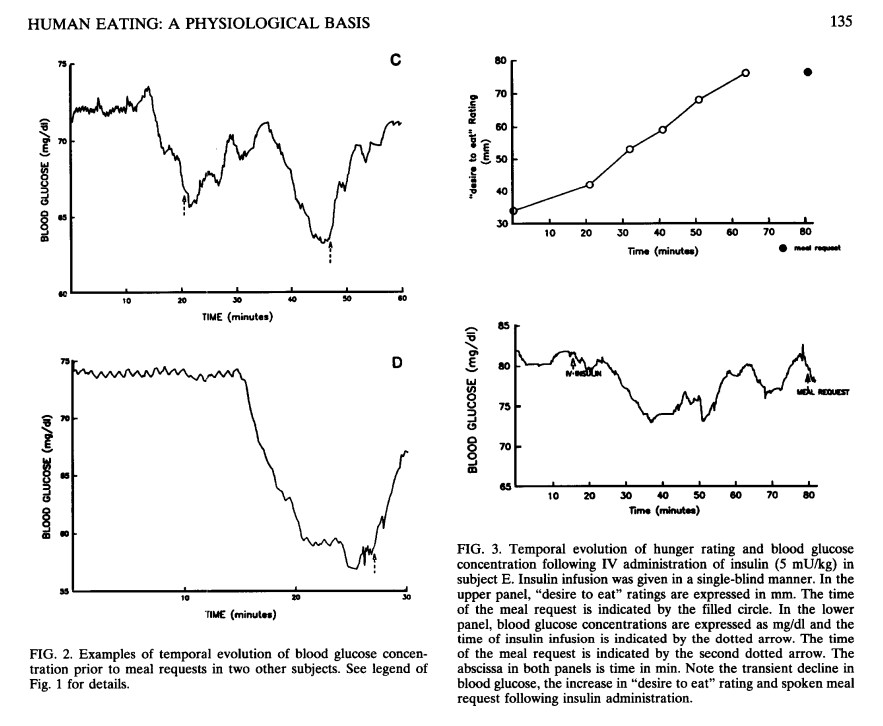
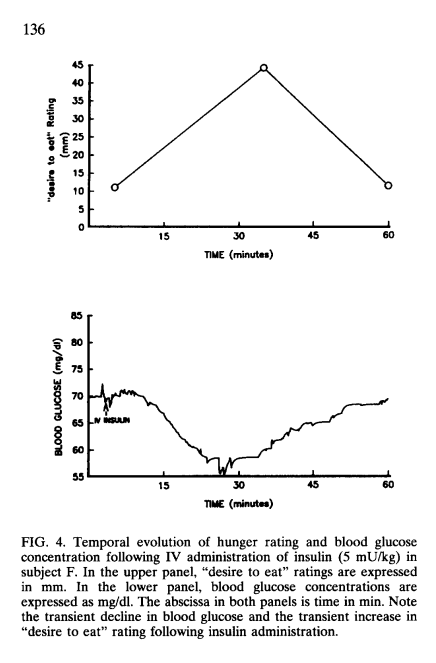
The idea that glucose patterns help regulate eating dates back at least to Jean Mayer's glucostatic theory in 1953.[1] Later human experiments by Campfield and colleagues found that transient declines in glucose frequently preceded meal initiation.[2]
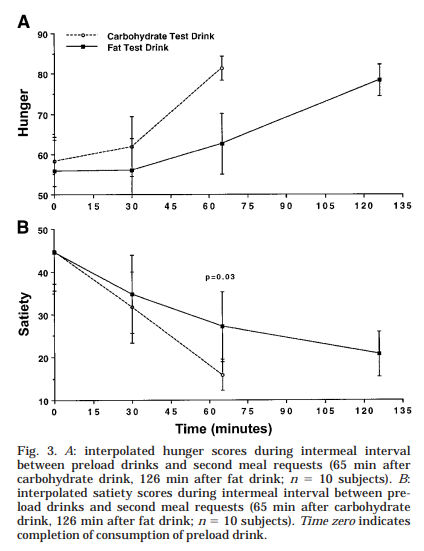
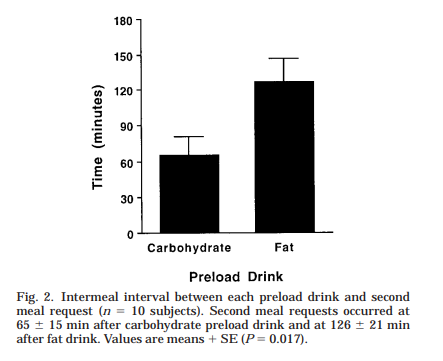
In a time-blinded feeding experiment, Melanson and colleagues compared taste-matched, energy-matched drinks with different carbohydrate and fat contents. The glucose patterns that followed the drinks were associated with meaningful differences in appetite and the timing of eating.[3]
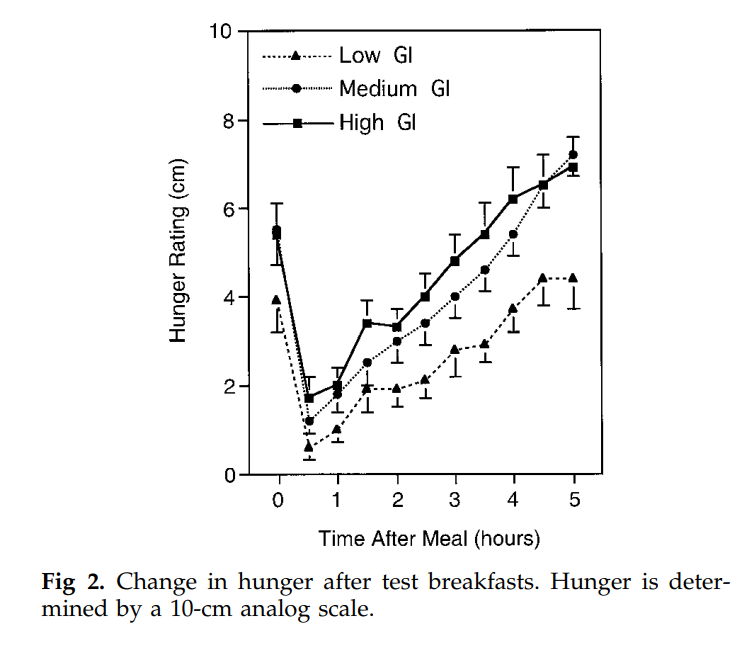
David Ludwig and colleagues then compared meals with different glycemic effects in boys with obesity. The high-glycemic-index meal was followed by greater hunger and greater voluntary food intake than the lower-glycemic meal.[4]
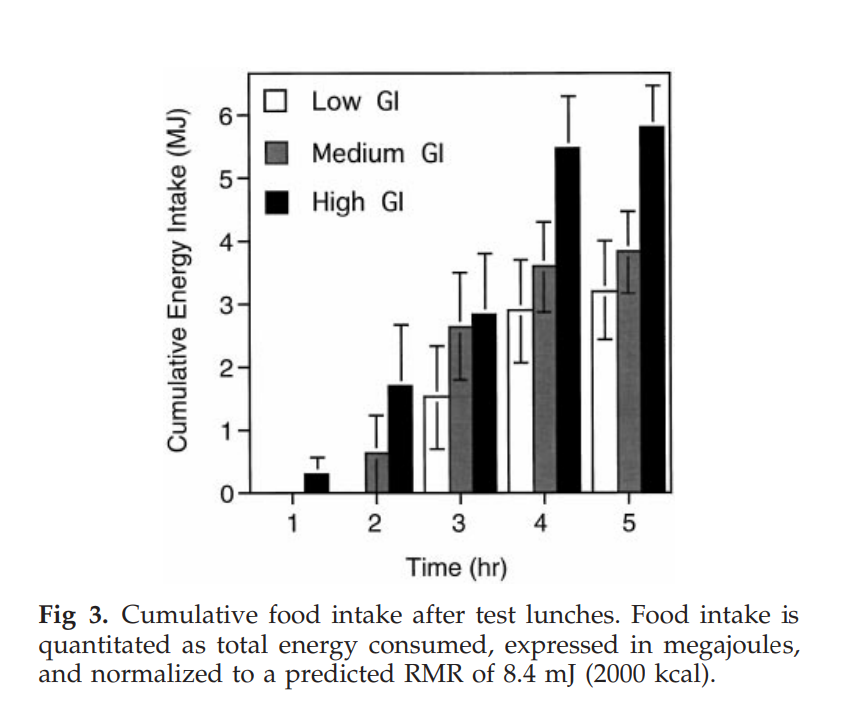
Together, these studies challenged the idea that calories alone determine how satisfied someone will feel. Energy matters, but the metabolic response to a meal can influence how difficult or easy it is to wait for the next one.
More figures from these studies
A glucose dip can change how the brain responds to food
The brain continuously monitors whether energy is available. When circulating glucose declines, that signal can change the balance between brain regions involved in reward and those involved in restraint.
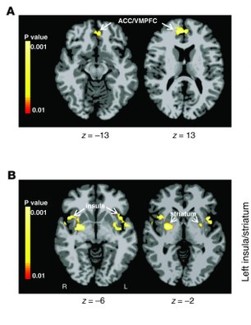
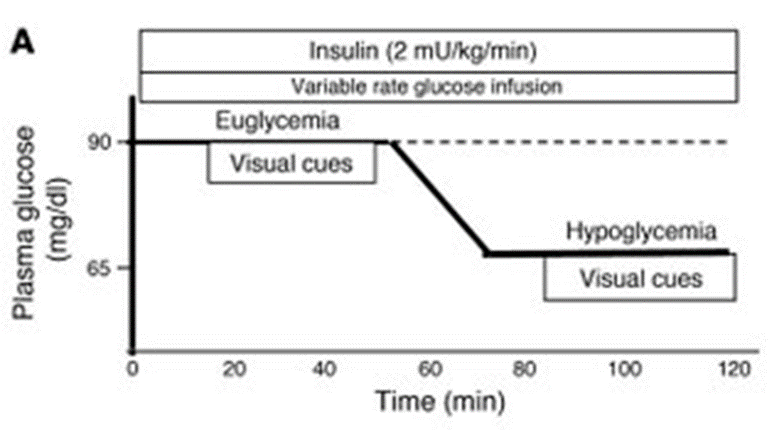
In a controlled Yale experiment, Page and colleagues used glucose clamps and functional MRI to compare euglycemia with a modest decline into the mild hypoglycemic range. Lower glucose activated limbic and striatal regions involved in reward and increased the desire for high-calorie foods. Maintaining normal glucose activated the medial prefrontal cortex, a region involved in regulation and decision-making. The restraining response was reduced in participants with obesity.[5]
This helps explain a common experience: food can become more compelling during a glucose decline, even when a person recently ate enough energy. The change is not imaginary, and it is not simply a conscious decision to disregard a plan.
Research in free-living adults adds another layer. Kim and colleagues found that people with obesity consumed more food in response to a similar pre-meal glucose nadir than people without obesity.[7] The glucose signal may therefore interact with obesity, insulin resistance, and the brain's response to food rather than affecting every person identically.
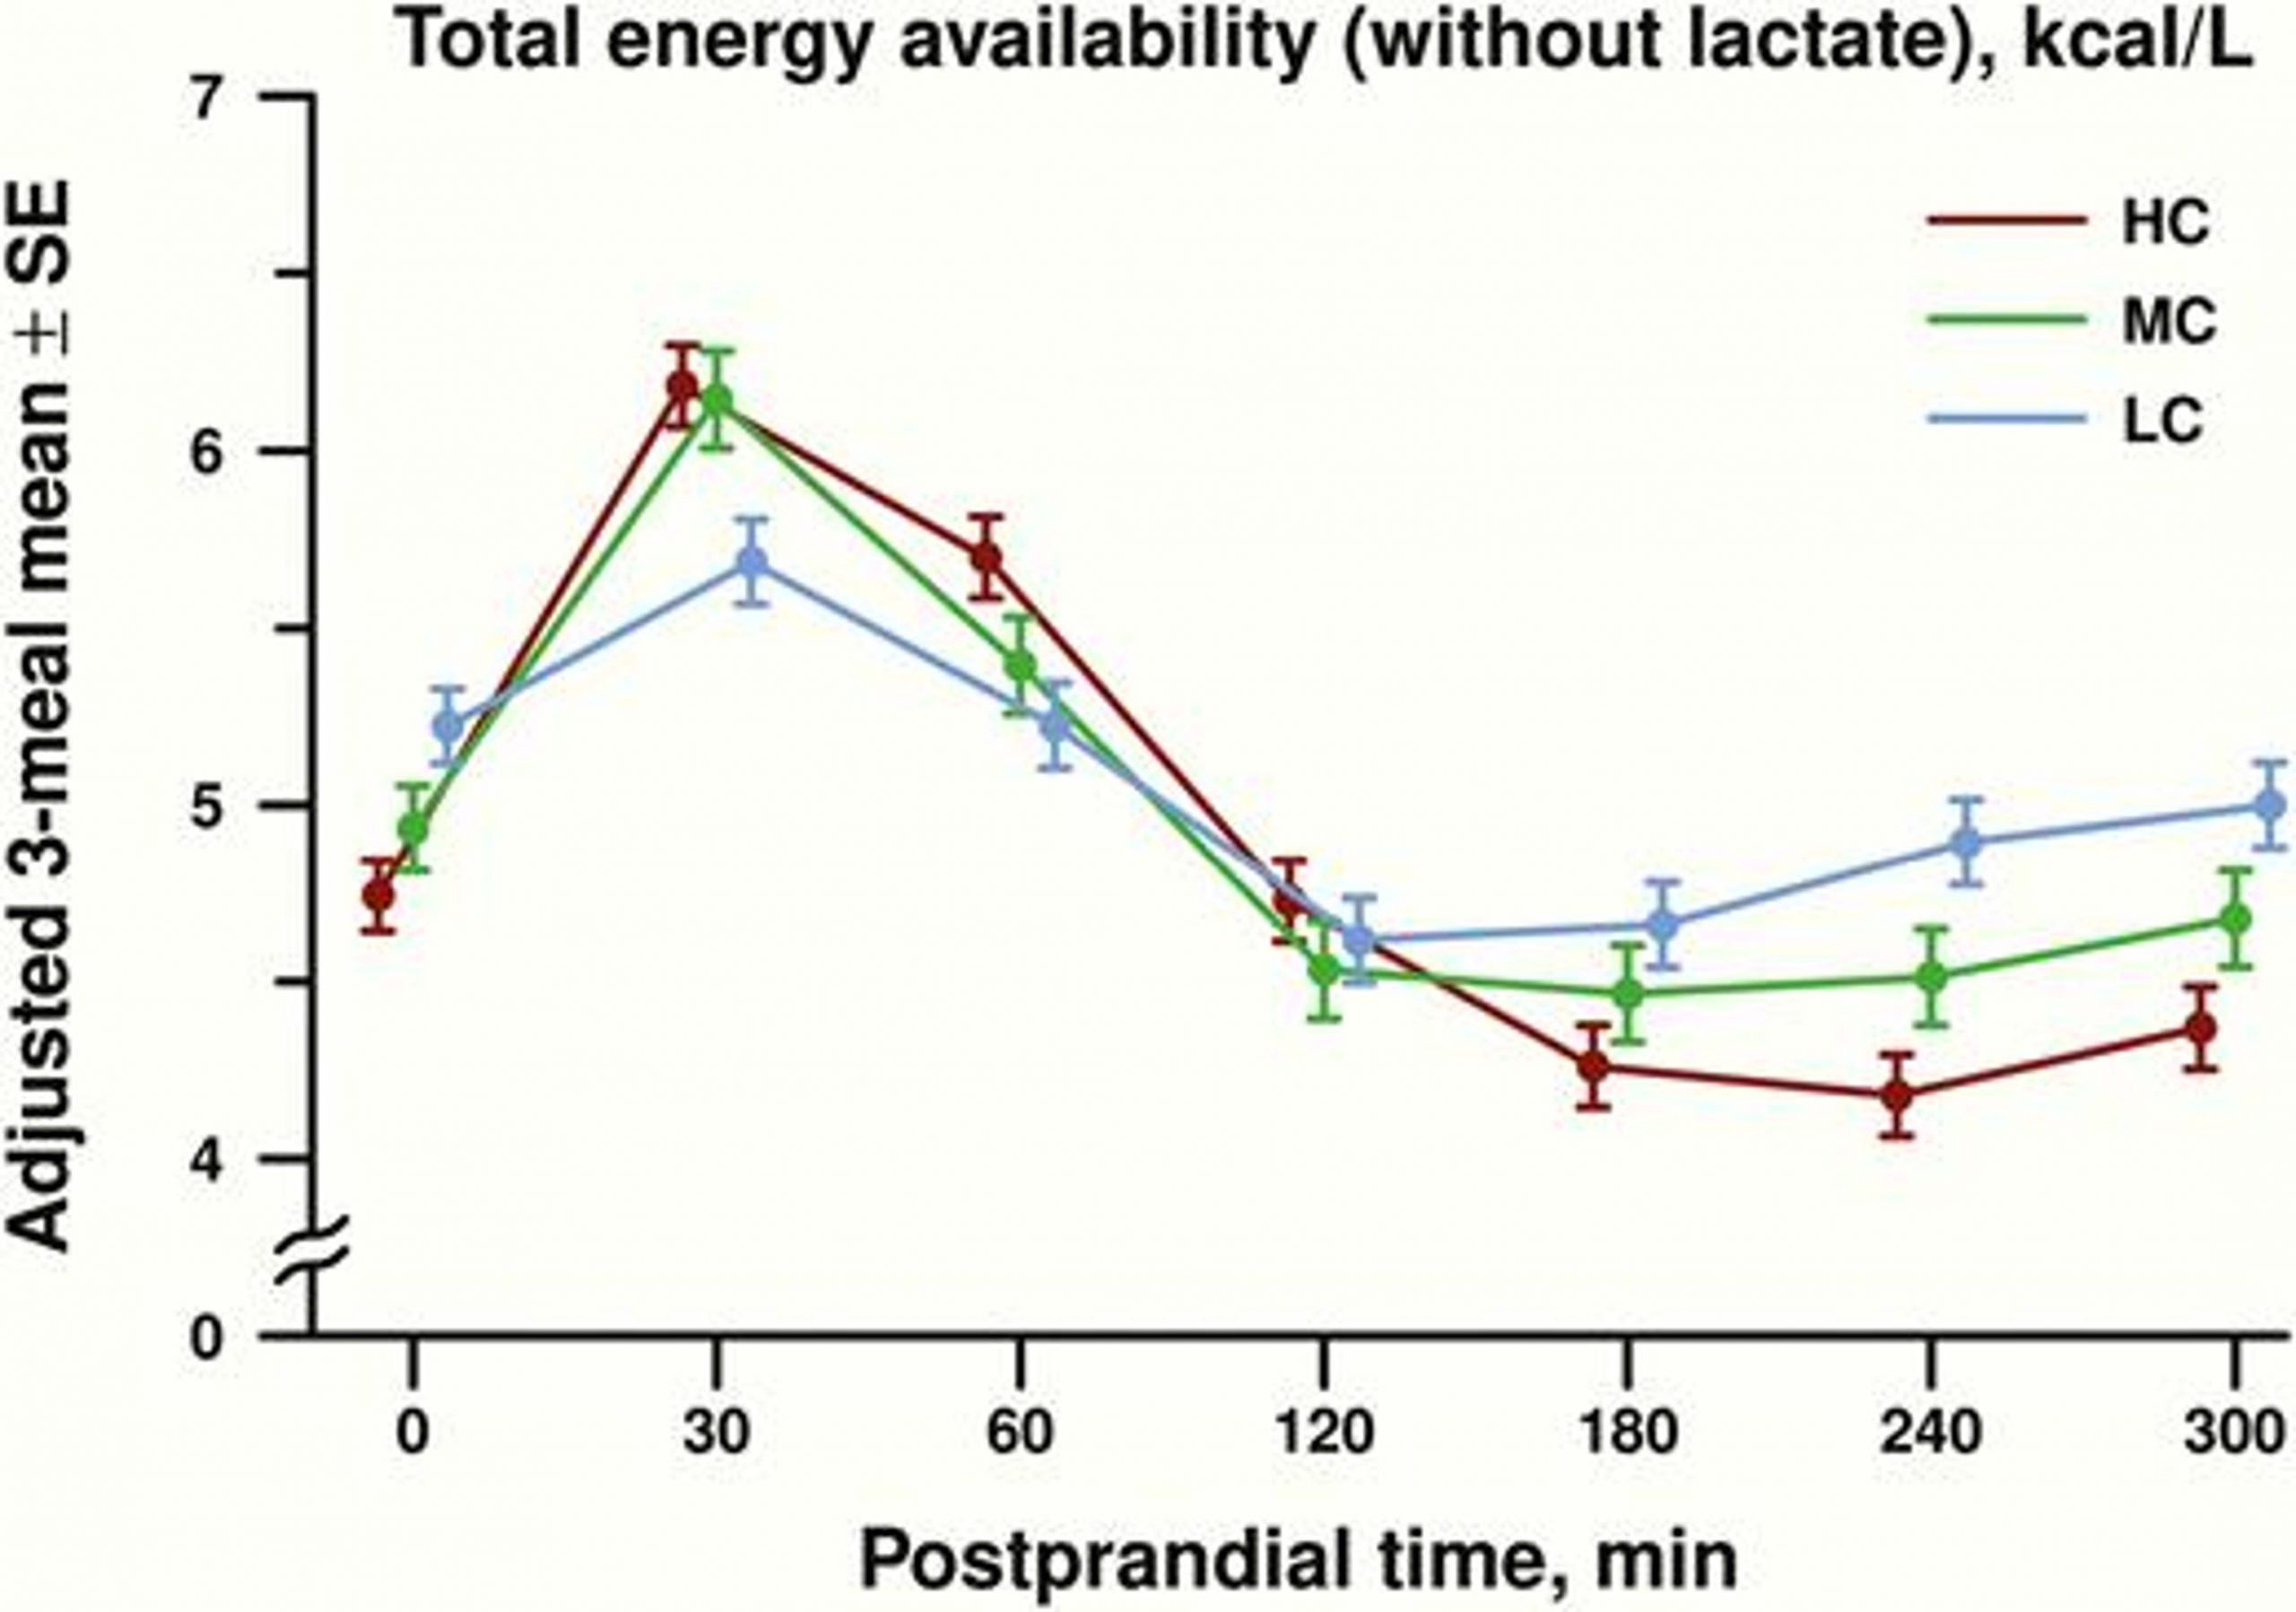
Glucose is not the only fuel available to the brain. In a controlled feeding study, Shimy and colleagues found that dietary carbohydrate content changed the combined availability of glucose, free fatty acids, and ketones after a meal.[6] Their results support a broader model in which appetite can respond to the availability of circulating metabolic fuels, not merely to a single glucose reading.
More figures from these studies
The largest real-world study connected post-meal dips with later hunger
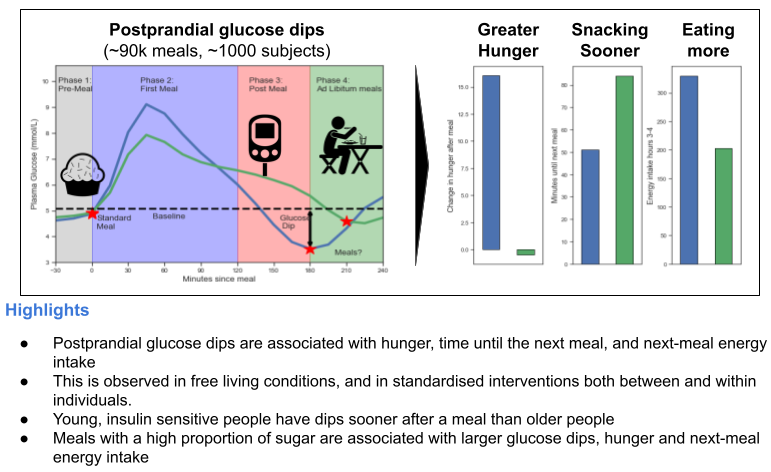
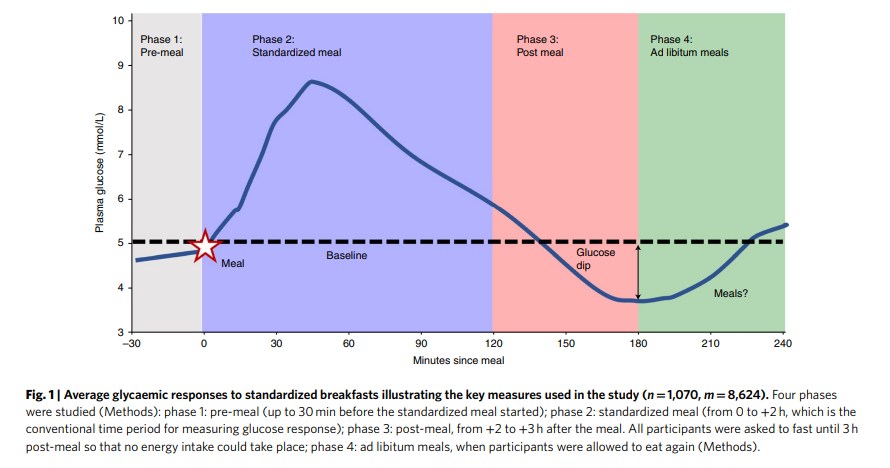
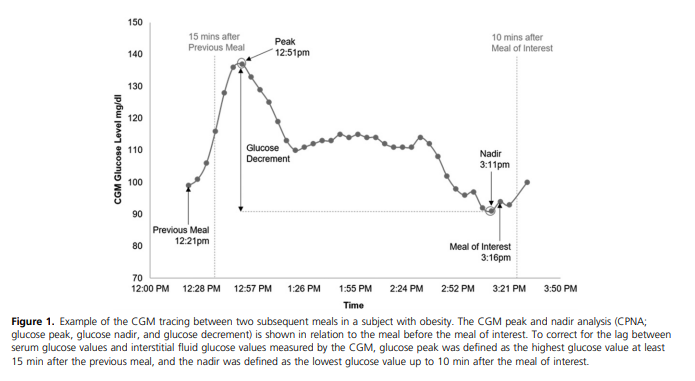
The 2021 PREDICT analysis by Wyatt and colleagues followed 1,070 participants who consumed 8,624 standardized meals and 71,715 meals of their own choosing while wearing continuous glucose monitors.[8]
Glucose dips two to three hours after a standardized meal predicted:
- greater hunger;
- less time until the next meal;
- greater energy intake three to four hours later; and
- greater total energy intake over 24 hours.
The dip was a better predictor of later hunger and intake than the early glucose peak or the early two-hour glucose response. This distinction matters. A person may focus only on the highest number after eating, while the later downward movement may be more closely connected to the urge to eat again.
The study was observational, so it does not prove that every glucose dip directly causes every episode of hunger. It does, however, provide large-scale, real-world support for the physiological pattern described in the earlier experiments.
More figures from these studies
Carbohydrate reduction can change appetite and cravings
Reducing sugar and refined starch usually reduces the amount of glucose entering the circulation after a meal. When carbohydrate restriction is combined with adequate protein, minimally processed foods, and meals that produce lasting satiety, many people experience fewer abrupt hunger signals and less persistent food-seeking.
Randomized trials support that experience.
In a two-year comparison of low-carbohydrate and low-fat diets, Martin and colleagues found that the low-carbohydrate group had greater decreases in cravings for carbohydrates and starches, lower preferences for high-carbohydrate and high-sugar foods, and less hunger.[9]
In a year-long randomized trial, Hu and colleagues found that peptide YY, a satiety-related hormone, decreased more with the low-fat diet. The findings suggest that a low-carbohydrate pattern may better preserve some satiety signals during weight loss, even though self-reported appetite and ghrelin did not differ significantly between the groups.[10]
These studies do not reduce hunger to a single glucose value. Protein intake, ketosis, food processing, energy balance, meal timing, and the reward value of food all matter. The practical point is that carbohydrate reduction can address both the metabolic signal and the subjective experience of cravings.
More figures from these studies
What glucose stability can mean for type 2 diabetes
For someone with type 2 diabetes, the goal is larger than avoiding an afternoon craving. Lowering post-meal hyperglycemia, improving time in range, and reducing A1C can be important parts of preventing diabetes-related complications.
In a crossover trial of 23 adults with type 2 diabetes, a low-carbohydrate breakfast reduced the glucose rise after breakfast and improved 24-hour glycemic variability.[11]
In a 12-month randomized quality-improvement program, adults with suboptimally controlled type 2 diabetes were offered intermittent CGM use plus personalized counseling targeting fewer than 100 grams of carbohydrate per day. A1C fell 0.41 percentage points more than with usual care in the intention-to-treat comparison. Among the participants who engaged and wore a CGM, A1C was 1.1 percentage points lower at 12 months than at baseline.[12]
The 2025 IGNITE trial randomized 163 adults with type 2 diabetes to CGM or blood-glucose monitoring during a medically supervised ketogenic program. Time in range, A1C, medication intensity, body weight, and carbohydrate intake improved in both groups. CGM was not superior to blood-glucose monitoring for the primary comparison, which reinforces an important point: the monitor can provide feedback, but the nutrition and medical-care program drives much of the change.[13]
Toward Health researchers have also examined the intersection of glucose control and food-addiction symptoms. In a 2026 pilot mixed-methods study of a 14-week group medical visit program, mean glucose decreased, time in range increased, and all six participants who met the study's food-addiction symptom threshold at baseline reported lower symptom counts afterward.[18] This creates an important bridge between metabolic signals and the behavioral experience of eating without turning either one into the entire explanation.
Why glycemia matters beyond hunger
The glucose dip that predicts hunger is not the same measurement as chronic hyperglycemia or long-term A1C variability. Those concepts should not be collapsed into one number. They do, however, show why glucose patterns matter across different time horizons.
In a controlled clamp experiment, Ceriello and colleagues found that oscillating high glucose produced greater endothelial dysfunction and oxidative stress than sustained high glucose in both participants with and without type 2 diabetes.[14] This was a short mechanistic study, not a cardiovascular-outcomes trial, but it demonstrated that glucose movement can produce measurable vascular effects.
Longer-term randomized evidence comes from the UK Prospective Diabetes Study. In 3,867 people with newly diagnosed type 2 diabetes, intensive glucose control reduced microvascular endpoints by 25% over ten years compared with conventional care.[15] Extended follow-up found that the benefits of early intensive control persisted. Sulfonylurea- or insulin-based intensive control was associated with relative risk reductions of 10% for death from any cause, 17% for myocardial infarction, and 26% for microvascular disease over the extended follow-up.[16]
Long-term variation in A1C and fasting glucose has also been associated with higher all-cause mortality in observational analyses of people with type 2 diabetes.[17] That association should not be interpreted to mean that flattening every small CGM fluctuation will prevent death. It supports the broader clinical value of achieving durable, safe glycemic control.
What a CGM can and cannot tell you
A continuous glucose monitor can help identify patterns that a single glucose measurement misses. It can show how a particular meal, sleep disruption, stress, activity, medication, or meal sequence affects glucose over several hours.
When you look at a recurring hunger pattern, use the readings to ask:
- How high did glucose rise after the meal?
- How quickly did it fall?
- When did hunger or cravings appear?
- Did the same meal create the same pattern more than once?
- What changed when protein, carbohydrate amount, food processing, or meal timing changed?
A CGM should not become a scorecard for judging every bite, and a single spike does not diagnose a disease. For more on time in range, glycemic variability and monitor data, read What Is a CGM?.
How to make hunger more predictable
The goal is not to chase a perfectly flat line. It is to build meals and routines that make hunger quieter, more predictable, and easier to distinguish from a craving or learned cue.
The strategies below bring food choices, daily routines and medical support together:
- prioritize protein at meals;
- reduce sugar, refined grains, and other rapidly absorbed carbohydrates;
- choose minimally processed foods that require more chewing and provide greater satiety;
- add nonstarchy vegetables, fiber, and whole-food fats according to tolerance and goals;
- notice whether a recurring meal is followed by sleepiness, urgent hunger, or cravings two to four hours later;
- use CGM or structured glucose checks when clinically appropriate;
- address sleep, stress, emotional eating, and food cues rather than expecting nutrition to solve every driver; and
- work with a clinician when glucose-lowering medication may need to be adjusted.
That final point is essential. Reducing carbohydrate intake can lower glucose quickly. Anyone taking insulin, a sulfonylurea, or another medication that can cause hypoglycemia may need prompt medical supervision and medication adjustment.
Hunger is information, not a character flaw
Calories still matter, but calorie awareness does not explain why one meal leaves you satisfied and another makes food feel urgent again.
The useful next step is to connect what you notice about meals, hunger and cravings with the strategies above and your own care plan.
Related video: How Blood Sugar Fluctuations Make You Hungry
Dr. Tro Kalayjian’s original 14-minute, 27-second video accompanies this article.
Video source: Glycemia + Hunger
References
- Mayer J. Glucostatic mechanism of regulation of food intake. New England Journal of Medicine. 1953;249(1):13-16. doi: 10.1056/NEJM195307022490104. ↩1↩2
- Campfield LA, Smith FJ, Rosenbaum M, Hirsch J. Human eating: evidence for a physiological basis using a modified paradigm. Neuroscience & Biobehavioral Reviews. 1996;20(1):133-137. doi: 10.1016/0149-7634(95)00043-E. ↩1↩2
- Melanson KJ, Westerterp-Plantenga MS, Saris WH, Smith FJ, Campfield LA. Blood glucose patterns and appetite in time-blinded humans: carbohydrate versus fat. American Journal of Physiology. 1999;277(2):R337-R345. doi: 10.1152/ajpregu.1999.277.2.R337. ↩1↩2
- Ludwig DS, Majzoub JA, Al-Zahrani A, Dallal GE, Blanco I, Roberts SB. High glycemic index foods, overeating, and obesity. Pediatrics. 1999;103(3):e26. doi: 10.1542/peds.103.3.e26. ↩1↩2
- Page KA, Seo D, Belfort-DeAguiar R, et al. Circulating glucose levels modulate neural control of desire for high-calorie foods in humans. Journal of Clinical Investigation. 2011;121(10):4161-4169. doi: 10.1172/JCI57873. ↩1↩2↩3
- Shimy KJ, Feldman HA, Klein GL, et al. Effects of dietary carbohydrate content on circulating metabolic fuel availability in the postprandial state. Journal of the Endocrine Society. 2020;4(7):bvaa062. doi: 10.1210/jendso/bvaa062. ↩1↩2
- Kim J, Lam W, Wang Q, et al. In a free-living setting, obesity is associated with greater food intake in response to a similar pre-meal glucose nadir. Journal of Clinical Endocrinology & Metabolism. 2019;104(9):3911-3919. doi: 10.1210/jc.2019-00240. ↩1↩2↩3
- Wyatt P, Berry SE, Finlayson G, et al. Postprandial glycaemic dips predict appetite and energy intake in healthy individuals. Nature Metabolism. 2021;3(4):523-529. doi: 10.1038/s42255-021-00383-x. ↩1↩2↩3
- Martin CK, Rosenbaum D, Han H, et al. Change in food cravings, food preferences, and appetite during a low-carbohydrate and low-fat diet. Obesity. 2011;19(10):1963-1970. doi: 10.1038/oby.2011.62. ↩
- Hu T, Yao L, Reynolds K, et al. The effects of a low-carbohydrate diet on appetite: a randomized controlled trial. Nutrition, Metabolism and Cardiovascular Diseases. 2016;26(6):476-488. doi: 10.1016/j.numecd.2015.11.011. ↩
- Chang CR, Francois ME, Little JP. Restricting carbohydrates at breakfast is sufficient to reduce 24-hour exposure to postprandial hyperglycemia and improve glycemic variability. American Journal of Clinical Nutrition. 2019;109(5):1302-1309. doi: 10.1093/ajcn/nqy261. ↩
- Griauzde DH, Ling G, Wray D, et al. Continuous glucose monitoring with low-carbohydrate nutritional coaching to improve type 2 diabetes control: randomized quality improvement program. Journal of Medical Internet Research. 2022;24(2):e31184. doi: 10.2196/31184. ↩
- Willis HJ, Asche SE, McKenzie AL, et al. Impact of continuous glucose monitoring versus blood glucose monitoring to support a carbohydrate-restricted nutrition intervention in people with type 2 diabetes. Diabetes Technology & Therapeutics. 2025;27(5):341-356. doi: 10.1089/dia.2024.0406. ↩
- Ceriello A, Esposito K, Piconi L, et al. Oscillating glucose is more deleterious to endothelial function and oxidative stress than mean glucose in normal and type 2 diabetic patients. Diabetes. 2008;57(5):1349-1354. doi: 10.2337/db08-0063. ↩
- UK Prospective Diabetes Study Group. Intensive blood-glucose control with sulphonylureas or insulin compared with conventional treatment and risk of complications in patients with type 2 diabetes: UKPDS 33. Lancet. 1998;352(9131):837-853. PubMed PMID 9742976. ↩
- Adler AI, Coleman RL, Leal J, Whiteley WN, Clarke P, Holman RR. Post-trial monitoring of a randomised controlled trial of intensive glycaemic control in type 2 diabetes extended from 10 years to 24 years: UKPDS 91. Lancet. 2024;404(10448):145-155. doi: 10.1016/S0140-6736(24)00537-3. ↩
- Kaze AD, Santhanam P, Erqou S, Ahima RS, Echouffo-Tcheugui JB. Long-term variability of glycemic markers and risk of all-cause mortality in type 2 diabetes: the Look AHEAD study. BMJ Open Diabetes Research & Care. 2020;8(2):e001753. doi: 10.1136/bmjdrc-2020-001753. ↩
- Johnson DJ, Buchanan LA, Saner EM, Calkins MW, Kirk JK. Psychological aspects and implications of food addiction and glucose control in type 2 diabetes: a pilot mixed-methods study. Healthcare. 2026;14(4):420. doi: 10.3390/healthcare14040420. ↩
Browse the diagrams, study excerpts, charts and news clipping that accompany the article. Each opens as an image for a closer look.
- Falling glucose and hunger: an illustrative curve
- Carbohydrates, insulin and hunger: a conceptual diagram
- Jean Mayer’s paper on glucose and food-intake regulation
- Morning blood-glucose patterns and hunger: historical charts
- News clipping on Coca-Cola research funding
- Human eating and physiology: the Campfield study excerpt
- Blood glucose, hunger ratings and meal requests: study charts
- Hunger ratings and blood glucose after insulin administration
- Hunger and satiety after carbohydrate and fat test drinks
- Time to the next meal after carbohydrate and fat test drinks
- Food intake after low-, medium- and high-glycemic-index meals
- Hunger ratings after low-, medium- and high-glycemic-index meals
- Glucose and the brain’s response to food: the Page study excerpt
- Glucose-clamp protocol and timing of visual food cues
- Brain-imaging results from the glucose and food-cue study
- Post-meal energy availability across dietary carbohydrate levels
- Example CGM tracing: glucose peak and dip between meals
- Glucose responses and study phases after a standardized breakfast
- Post-meal glucose dips, hunger and food intake: study overview